This page presents educational information originally published by the Tennessee Breast Center. It is general knowledge, not medical advice — read our full disclaimer.
Overview
Breast cancer is the most common malignancy in women and the second leading cause of cancer death (exceeded by lung cancer in 1985). Breast cancer is three times more common than all gynecologic malignancies put together. The incidence of breast cancer has been increasing steadily — from 1 in 20 women in 1960 to 1 in 8 women today.
The American Cancer Society estimated that 182,800 new cases of invasive breast cancer would be diagnosed in the year 2000, and 40,800 patients would die from the disease. Breast cancer is truly an epidemic among women, and we do not know why.
Breast cancer is not exclusively a disease of women. For every 100 women with breast cancer, one man will develop the disease — an estimated 1,500 men per year. The evaluation of men with breast masses is similar to that in women, including mammography.
The incidence of breast cancer is very low in the twenties, gradually increases and plateaus around age forty-five, and increases dramatically after fifty. Fifty percent of breast cancer is diagnosed in women over sixty-five, indicating the ongoing necessity of yearly screening throughout a woman’s life.
Breast cancer is a heterogeneous disease: it is a different disease in different women, in different age groups, and even within the tumor itself, which may contain different cell populations. Generally, breast cancer is a much more aggressive disease in younger women. Autopsy studies show that 2% of the population has undiagnosed breast cancer at the time of death. Older women typically have much less aggressive disease than younger women.
Risk Factors for Developing Breast Cancer
Early onset of menses and late menopause
Onset of the menstrual cycle before age 12 and menopause after 50 increase the risk of developing breast cancer.
Diets high in saturated fat
The types of fat matter. Monounsaturated fats such as canola oil and olive oil do not appear to increase risk the way polyunsaturated fats — corn oil and meat — do.
Family history of breast cancer
Patients with a positive family history are at increased risk. However, 85% of women with breast cancer have a negative family history. Family history here means immediate relatives: mother, sisters and daughters. If a family member was post-menopausal (fifty or older) at diagnosis, the lifetime risk increases only about 5%. If she was premenopausal, the lifetime risk is 18.6%; premenopausal and bilateral, 50%.
Women with a significantly positive family history of premenopausal breast cancer should begin screening mammography a decade sooner than the age at which their family member was diagnosed. BRCA-1 and BRCA-2 gene testing can identify patients at genetically increased risk for breast cancer as well as other epithelial tumors, including ovarian and colon cancer.
At the time this material was written, genetic testing was considered investigational. If a woman carries these genetic markers, should bilateral mastectomy and oophorectomy be recommended? Further, if her insurer knows she carries these markers, she may lose her coverage. If a woman decides to proceed with genetic testing, paying for the test individually keeps the results confidential.
Late or no pregnancies
Pregnancies prior to age twenty-six are somewhat protective. Nuns have a higher incidence of breast cancer.
Moderate alcohol intake
Greater than two alcoholic beverages per day.
Estrogen replacement therapy
Most studies indicate that taking estrogen longer than ten years may lead to a slight increase in breast cancer risk. However, the same studies indicate that the benefits of estrogen — reducing the risk of osteoporosis, heart disease, and (more recently documented) Alzheimer’s disease and colon cancer — far outweigh the slight risk that may be associated with estrogen replacement therapy.
Caution is warranted for women with a significantly positive family history of breast cancer or atypical intraductal hyperplasia. By convention, women with breast cancer are currently taken off estrogen replacement — there are no scientific studies justifying this practice, but until such studies are available, convention prevails.
History of prior breast cancer
Patients with a prior history of breast cancer are at increased risk of developing a new cancer in the other breast — about 1% per year, or a 10% lifetime risk. The reason for close clinical follow-up after a breast cancer diagnosis is not only to detect recurrence, but also to detect cancer in the opposite breast.
Female sex
Being female itself increases risk. Still, for every 100 women with breast cancer, one man develops the disease.
Therapeutic irradiation to the chest wall
Patients treated with chest irradiation (for example, for Hodgkin’s disease) are at increased risk of developing breast cancer approximately ten years later; earlier screening should be considered in this population.
Moderate obesity
The relationship of breast cancer to obesity is complex, but obesity is associated with an increased risk.
Breast Cancer Types
Ductal carcinoma in situ (DCIS)
Generally divided into comedo (the cut surface of the tumor extrudes dead and necrotic tumor cells, similar to a blackhead) and non-comedo types. DCIS is early breast cancer confined to the inside of the ductal system. The distinction matters because comedocarcinoma in situ generally behaves more aggressively and may show areas of microinvasion through the ductal wall.
Surgical management is the same as for other types of breast cancer except that axillary node sampling is not done, since only 1% of these lesions have axillary metastasis. Irradiation is recommended after conservative breast surgery, reducing recurrence from 21% without irradiation to 5%–10% with it — at the time of writing, a controversial area of treatment.
Infiltrating ductal carcinoma
The most common type, representing 78% of all breast malignancies. These lesions can be stellate (star-like on mammography) or well circumscribed (rounded). The stellate lesions generally carry a poorer prognosis.
Medullary carcinoma
Comprises 15% of breast cancers. Generally well circumscribed and sometimes difficult to distinguish from a fibroadenoma by mammography or sonography. Medullary carcinoma is estrogen- and progesterone-receptor negative 90% of the time, and usually has a better prognosis than ordinary breast cancer.
Infiltrating lobular carcinoma
About 15% of breast cancers. These lesions generally present in the upper outer quadrant of the breast as a subtle thickening and are difficult to diagnose by mammography. They can be bilateral. Microscopically the cells line up in a row (“Indian filing”) and grow around ducts and lobules (“targeting”).
Tubular carcinoma
An orderly, well-differentiated carcinoma making up about 2% of breast cancers, with a favorable prognosis — nearly 95% ten-year survival.
Mucinous (colloid) carcinoma
Represents 1%–2% of breast carcinomas with a favorable prognosis; usually well circumscribed.
Inflammatory carcinoma
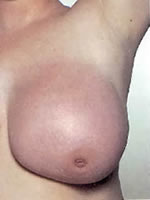
A particularly aggressive type. The breast skin becomes red (erythema), thickened, with prominent hair follicles resembling an orange peel (peau d’orange). Diagnosis is made by skin biopsy, which reveals tumor in lymphatic and vascular channels 50% of the time.
Prognostic Indicators
Tumor size
As tumor size increases, the risk of axillary and systemic metastasis increases.
Histologic grade
The appearance of the tumor cells under the microscope, graded 1) well differentiated, 2) moderately differentiated, 3) poorly differentiated. Survival diminishes with increasing grade.
Estrogen and progesterone receptors
Protein sites on the surface of tumor cells to which estrogen and progesterone bind; the complex moves inside the cell, driving division. The presence of these receptors is a good prognostic indicator — such tumors respond to hormonal therapy such as tamoxifen.
Axillary nodes
The most important prognostic indicator. Patients with microscopically negative axillary nodes have improved disease-free and long-term survival.
DNA flow cytometry
A test of the genetic material within the cell. Tumors with a normal amount of DNA (diploid) have better disease-free and long-term survival than those with an abnormal amount (aneuploid). The test also measures the fraction of cells in active division; tumors with under 10% active division have a better prognosis.
HER-2/neu
A protein product secreted by the tumor that indicates decreased disease-free and long-term survival.
Breast Cancer Staging (TNM)
| Code | Meaning |
|---|---|
| TX | Primary tumor cannot be assessed |
| TIS | Carcinoma in situ; Paget’s disease without a tumor |
| T0 | No evidence of primary tumor |
| T1 | Tumor 2 cm or less in greatest dimension |
| T2 | Tumor larger than 2 cm but not larger than 5 cm |
| T3 | Tumor larger than 5 cm |
| T4 | Tumor of any size extending to the chest wall or skin |
| Code | Meaning |
|---|---|
| N0 | No metastasis to axillary nodes |
| N1 | Metastasis to movable axillary nodes |
| N2 | Metastasis to fixed or matted axillary nodes |
| N3 | Metastasis to supraclavicular, infraclavicular or internal mammary nodes |
| M0 | No distant metastasis |
| M1 | Distant metastasis |
| Stage | Tumor (T) | Nodes (N) | Metastasis (M) |
|---|---|---|---|
| Stage 0 | TIS | N/A | M0 |
| Stage I | T1 | N0 | M0 |
| Stage II | T0 | N1 | M0 |
| T1 | N1 | M0 | |
| T2 | N0, N1 | M0 | |
| Stage IIIA | T0 | N2 | M0 |
| T1 | N2 | M0 | |
| T2 | N2 | M0 | |
| T3 | N0, N1, N2 | M0 | |
| Stage IIIB | Any T | N3 | M0 |
| T4 | Any N | M0 | |
| Stage IV | Any T | Any N | M1 |
Five-Year Survival Rate by Stage
| Stage | Survival rate |
|---|---|
| Stage 0 | 100% |
| Stage I | 98% |
| Stage II | 88% |
| Stage IIIA | 56% |
| Stage IIIB | 49% |
| Stage IV | 16% |